

|
Seasonal influenza is a very common and highly infectious virus. It can be much more severe than the common cold and may result in two or three days in bed, leading to missed work and school days.
For some at-risk groups (especially frail elderly people and individuals with certain health conditions), flu can be very dangerous. Flu complications may lead to more than ten thousand hospital stays and an average of 600 deaths in the UK every year, but this can vary. In 2012, there were 83 deaths from influenza in England and Wales, whereas in the 2024-2025 season in England, there were 9,740 deaths. In the 2025-26 flu season, there were 3,798 deaths from influenza. The flu virus constantly changes, so different strains circulate yearly. The World Health Organization monitors the virus throughout the world and advises which 3 or 4 strains should be covered by an annual flu vaccine. Flu vaccination is offered annually because the previous year's vaccine may not provide protection against the strains that circulate in a new season and because immunity needs to be boosted each year, even for the same strain. In the UK, the flu vaccine is available each year from September or October onwards. Eligible people are recommended to get their flu vaccine in the autumn or early winter before outbreaks begin. It takes up to two weeks after vaccination for protection to develop. Not only does the flu vaccine reduce your chances of getting the flu, it has also been shown to reduce the length of hospital stays and severe illness in those who do still get the illness. The UK Health Security Agency suggests that last year flu vaccination prevented around 100,000 hospitalisations and around 7,000 deaths. 
|
Flu vaccine
Vaccine
|
There is strong evidence that pregnant women have a much higher risk of serious illness because of flu, compared with the general population. The risks are highest in the last three months of pregnancy. Vaccination against the flu reduces the risk of complications caused by the virus for women and babies. Serious complications of flu include bronchitis, pneumonia, septic shock (a severe and life-threatening infection of the whole body), meningitis and encephalitis (inflammation of the brain). There is also strong evidence that catching the flu during pregnancy has an effect on the unborn baby. Babies born to women who have had flu are up to four times more likely to be born prematurely and to have a low birth weight. This may be because flu infection produces an inflammatory response in the body which can trigger premature labour. Flu in pregnancy can even lead to stillbirth or death in the first week of life.

A 2019 study with 20,000 pregnant women over six years in the United States, Australia, Israel, and Canada, showed that the flu vaccine provided a 40% reduction in hospitalisations from flu. A US study published in 2017 looked at the effects of flu vaccination in the first three months of pregnancy. They compared 52,000 babies who had been exposed to the flu vaccine in the first three months of pregnancy with over 370,000 babies who had not been exposed to the flu vaccine. The study showed that having the flu vaccine in early pregnancy was not associated with an increased risk of birth defects. Another US study published in 2026, which examined health records of over 42,000 mothers and infant pairs, found that flu infection in early pregnancy was associated with increased risks of negative birth outcomes, while vaccination reduced the risks of low birth weight and preterm birth. |
|
Adults receive inactive influenza vaccines by injection, which do not contain any live virus; they are offered the specific inactivated influenza vaccine that has been shown to be the most effective. If eligible, due to having certain long-term health conditions that mean they're unable to receive a live vaccine, children from 6 months to 2 years are offered an inactive influenza vaccine. Live flu vaccineVaccinated children shed the virus for a few days after vaccination through sneezing or coughing. However, the vaccine virus is weakened, so it is much less able to spread from person to person than flu viruses that normally spread. The amount of virus that children shed is normally below the levels needed to pass on the infection to others. The virus does not survive for long outside the body. It is not necessary for children to be off school during the period when the vaccine is being given. The only exception is the very small number of children who are extremely immunocompromised. These children are usually advised not to attend school anyway, because of the higher risk of being in contact with infections that spread in school. The nasal flu spray should not be given to anyone with a weakened immune system. This includes people who:
This is because the weakened viruses in the vaccine could replicate too much and cause infection. Children who have been vaccinated with the nasal spray should avoid close contact with people who have very severely weakened immune systems for about two weeks following vaccination. If it is not possible for a child to avoid contact with someone who is severely immunosuppressed, e.g because they live in the same house, the child should not receive the nasal flu vaccine. It may be possible for them to have the inactivated flu vaccine instead. How effective is the NHS flu immunisation programme?The flu vaccine works better in some years than others. Across all age groups including children, the flu vaccine prevented between 15 to 52% of flu cases between 2015 – 2020. Last year, estimates of vaccine impact indicated that the vaccination programme in England prevented between 86,900 and 125,100 hospital admissions and between 5,800 and 8,900 deaths. Vaccine coverage ranged from 71 to 75% for adults aged 65 years and above, 37 to 43% for younger adults with clinical risk factors, 45 to 55% for secondary school children, 55 to 67% for primary school children and 30 to 50% for pre-school children.
Do we need the flu vaccine every year?Having a flu vaccine every year is important because the flu virus is variable and changes over time. Each year there are different strains, and a new vaccine must be prepared to deal with them. Vaccination from previous years is not likely to protect people against current strains of flu. 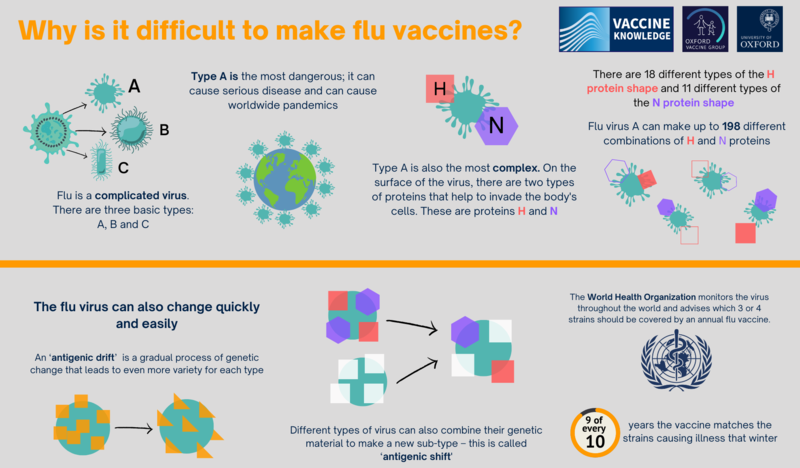
Click here for an accessible text version of this infographic
Each year’s flu vaccine is made to give the best protection against the strains of flu that are expected to circulate (spread) in the coming season. The trivalent vaccine protects against three of the flu virus strains which are most likely to be around. The quadrivalent vaccine protects against four flu virus strains. However, decisions about what to put in the flu vaccine must be made six months before the flu season starts. The JCVI, an expert advisory board in the UK, statement for 2025 to 2026 noted that the World Health Organization (WHO) has concluded that B/Yamagata lineages (a strain of flu) are no longer circulating and are unlikely to cause future epidemics, and that inclusion of a B/Yamagata antigen as a component of flu vaccines is no longer warranted, and so the trivalent vaccines (protects against three flu strains) will be used where possible. This has not changed for the 2026/27 flu season. Every February, the World Health Organisation (WHO) reviews the types of flu that have been circulating in all parts of the world and decides which ones will go into the vaccine for the following autumn. This allows time for the vaccine to be made – but it also gives the flu virus time to change before vaccination starts in the autumn. This means that sometimes the flu vaccine may not be a good match for all the strains of flu that are circulating. Read more about the WHO recommendations for the 2025-26 season. Researchers are investigating ways to create a flu vaccine that protects against the many different varieties of flu. If they are successful, it will mean that people will only need a single flu vaccine to give them lifelong protection, instead of having a yearly vaccine. However, it will be several years before we find out if it is possible to do this. The virus for the some flu vaccines is usually grown in hen’s eggs. This is a slow process and can lead to something called ‘egg adaptation’. The flu virus strain starts to adapt to the conditions in the egg, leading to changes in the virus. This is another reason that the flu vaccine may not always match the circulating strains of flu. Since 2018-19, a new vaccine has been developed using cell culture instead of eggs for flu seasons. This vaccine is less likely to adapt as it has been developed using cells that are very similar to human cells. The recombinant flu vaccine also does not use eggs in its manufacturing processes and is one of the types of flu vaccine that is recommended for use over the age of 18 years. |

